Buy Medrol online in 4 mg tablets, a methylprednisolone course that settles a flare quickly and steps down from six tablets a day to just one. Most prescriptions arrive as a printed card of 21 tablets rather than a bottle. The count on that card drops every day. The whole plan is built to finish inside a week.
On this page
- The Steroid Behind the Medrol Dose Pack
- Counting Down the 21 Tablets in a Dosepak
- Back-to-Back Dose Packs and the Safe Gap
- How Fast the Dose Pack Starts Working
- Buy Medrol Online and What Each Pack Costs
- Medrol Tablet Strengths From 4 mg to 32 mg
- Optic Neuritis and the Oral High-Dose Option
- Side Effects Most People Notice by Day Two
- Who Should Wait Before Starting a Course
- Medications That Clash With Methylprednisolone
The Steroid Behind the Medrol Dose Pack
Medrol is the brand name for methylprednisolone tablets. The medication is a corticosteroid. It copies cortisol, the hormone the adrenal glands release each morning. That copy holds inflammation down much harder than the original. At the same number of milligrams it works about five times as strongly.
The word steroid causes confusion here. This is not the kind that builds muscle. Glucocorticoids quiet the immune system, while anabolic steroids act on tissue growth. They share a chemical family and very little else.
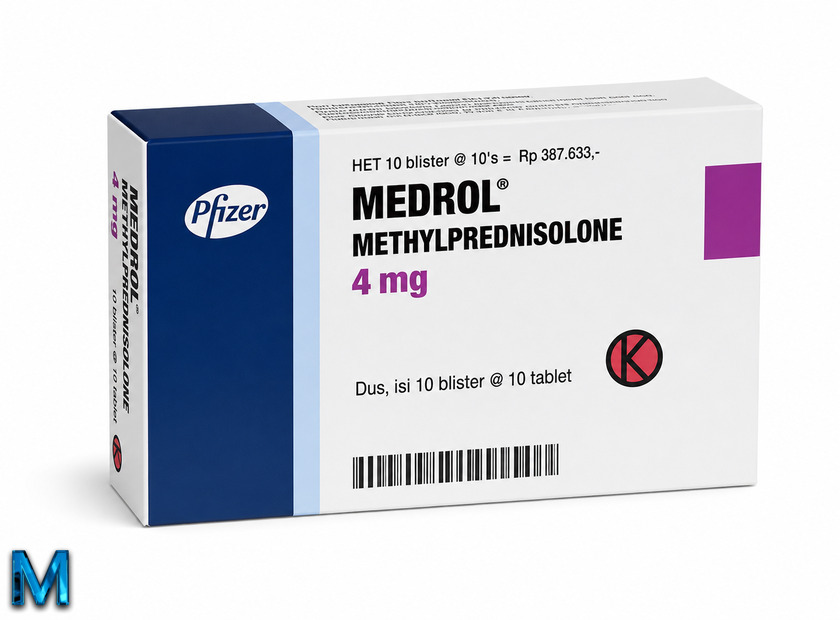
Most people meet this medication as a Dosepak instead of a bottle. That is a foil card holding 21 small tablets of 4 mg each. Every row on the card belongs to one day. The number of tablets in each row falls as the week goes on. Patients who buy Medrol online for a familiar flare order that same pack.
One action explains everything the tablets do. Methylprednisolone slips inside a cell and switches off the genes that produce inflammatory signals. Fewer signals go out, so fewer immune cells arrive at the site. Swelling drops wherever that reaction was running.
Conditions That Put Medrol on a Prescription
A short pack is written for a flare that has broken through whatever was holding it. The illness itself matters less than the immune reaction driving it. That is why one small card covers so much ground:
- Asthma attacks and severe allergic reactions
- Poison ivy and other severe skin rashes
- Gout attacks and inflamed tendons or joints
- Sinus swelling that will not settle after an infection clears
- Nerve pain from a disc pressing on the spine
- Hives that outlast a week of antihistamines
- Relapses in multiple sclerosis and inflammation inside the eye
Back trouble is the entry on that list with the weakest evidence behind it. Steroid tablets were tested against a dummy pill in people with sciatica from a slipped disc. Function improved a little and pain did not move at all, while side effects roughly doubled. Doctors still prescribe them, though the aim is getting moving again rather than a quiet back.
Long-running conditions use the same tablets in a different rhythm. Lupus, rheumatoid arthritis and bowel disease are treated from an ordinary bottle at a steady daily dose. The six-day card suits a problem with a beginning and an end.
Counting Down the 21 Tablets in a Dosepak
A Dosepak is six days of treatment printed on one card. It holds 21 tablets at 4 mg each. Day one uses six of them and day six uses a single tablet. Nothing is left over when the course ends.
The falling count is the whole design. Treatment opens at 24 mg, which is high enough to break a flare quickly. Each following day removes one tablet, so the dose steps down on its own. By the last morning the amount left is close to what the body makes anyway.
Added up, the pack delivers 84 mg across the week. That total is modest for a corticosteroid. The course can therefore stop on the sixth evening. No separate wind-down is needed.
What to Take on Each of the Six Days
Six tablets on day one, then five, four, three, two and one. The card spreads each day across meals and bedtime, and the printed rows look like this:
| Day | Tablets | How the card splits them | Total |
|---|---|---|---|
| Day 1 | 6 | 2 before breakfast, 1 after lunch, 1 after supper, 2 at bedtime | 24 mg |
| Day 2 | 5 | 1 before breakfast, 1 after lunch, 1 after supper, 2 at bedtime | 20 mg |
| Day 3 | 4 | 1 before breakfast, 1 after lunch, 1 after supper, 1 at bedtime | 16 mg |
| Day 4 | 3 | 1 before breakfast, 1 after lunch, 1 at bedtime | 12 mg |
| Day 5 | 2 | 1 before breakfast, 1 at bedtime | 8 mg |
| Day 6 | 1 | 1 before breakfast | 4 mg |
Plenty of prescribers now change that pattern. They ask patients to take the whole day’s count in the morning, because the bedtime tablets are what ruin sleep. Your own cortisol peaks shortly after waking, so a morning dose lands on a signal the body expects. Follow whichever plan came with the prescription rather than mixing the two.
A plain bottle of 4 mg tablets works the same way. Loose 4 mg tablets copy the printed schedule exactly. The card is convenience rather than pharmacy. Six tablets counted by hand on day one do exactly what the printed row does.
Back-to-Back Dose Packs and the Safe Gap
A second pack the morning after the first is not a call to make at home. No limit is printed on the card, which is exactly why the question comes up so often. A prescriber can extend treatment and often does. The decision follows a look at why the first course fell short.
A flare that returns on day seven usually means something else needs attention. Asthma that keeps breaking through points to daily control being too light. A rash that flares again may still be meeting whatever set it off. Repeating the pack without answering that question buys another week at best.
Six days is too short to send the adrenal glands to sleep. Suppression becomes a real concern around the three-week mark, so one pack ends cleanly with no step-down. Two packs run together sit closer to that line and change the calculation.
A second course usually looks different from the first when a prescriber does approve one. The opening dose runs higher or the step-down stretches longer, since a flare that shrugged off six days rarely yields to an identical week. Blood pressure and glucose get more attention the second time around.
Frequency across the year matters more than any single gap. Bone density, blood glucose and eye pressure respond to the total amount taken, not to how it was divided. Three or four short courses in twelve months changes the picture. Most clinicians then look for a treatment that prevents flares.
How Fast the Dose Pack Starts Working
Blood levels peak one to two hours after the first tablets. Relief arrives later than that. Hives and asthma usually ease within four to twelve hours. Joint and nerve pain take a day or two, and stubborn sinus swelling can need the full course.
The delay comes from how the medication works. Nothing gets blocked on contact. Cells are told to stop making inflammatory proteins, and the ones already circulating still have to burn out. A rough timeline looks like this:
- First evening: itching and wheeze often lighter, swelling barely changed
- Day two: redness fading and movement easier in a sore joint
- Day three: most of the benefit from the course is usually visible
- Day six: symptoms low enough that the last tablet feels unnecessary
Speed also depends on where the inflammation sits. Tissue with a rich blood supply answers first, which is why skin and airways settle before a sore joint does. Swelling packed into a narrow space takes the longest. A blocked sinus can feel heavy on day four while a rash has already faded.
Day six is where a common mistake happens. People stop at day four because the problem looks solved, and the flare returns two days later. The last tablets carry the smallest doses and hold the ground the first ones took.
Three days with no change at all is worth reporting. Some conditions simply do not answer to corticosteroids, and pushing the dose higher only adds unwanted effects. People buy Medrol online for a recurring problem precisely because they know by now how their own flare behaves.
Buy Medrol Online and What Each Pack Costs
Methylprednisolone is prescription-only in the United States and no licensed pharmacy sells it otherwise. Online packs are counted in tablets rather than six-day cards, so one course works out at 21 of them. Anyone planning to buy Medrol online should match the strength to the prescription before picking a pack size.
Per-tablet pricing is the only fair way to compare listings. Each row below carries two figures. The crossed-out number is the standard total for that pack, and the bold one is what the order comes to.
| Strength | Pack size | Per tablet | You save | Per pack |
|---|---|---|---|---|
| Medrol 4 mg | 120 tablets | $0.78 | $45.33 | |
| Medrol 4 mg | 360 tablets | $0.69 | $166.21 | |
| Medrol 16 mg | 90 tablets | $2.39 | $141.72 | |
| Medrol 16 mg | 270 tablets | $1.86 | $566.89 |
One course is a small share of any pack in that table. A 120 tablet order of the 4 mg strength covers five separate flares at $16 or so each. The price Medrol carries per tablet keeps falling as the pack grows. Larger sizes therefore look very different at the checkout.
Retail pharmacies price the same tablets across a wide range. Two counters in one city can differ several times over on cash price, and almost nobody calls around to check. Insurance is not automatically the cheaper route either. A copay on a generic tier can land above the cash figure. That happens most while a deductible is unmet.
Fixed pricing is the practical draw here. The cost Medrol adds to a flare is fixed the moment the order goes through. No counter price changes it afterward. Certainty is why people buy Medrol online for a condition that flares twice a year.
Four Steps From Online Consult to Delivery
Searches for a way to buy Medrol without prescription turn up daily, and the answer is short. A telehealth consultation is the legitimate route to that prescription, not a way around one. Four steps cover the whole process:
- Describe the flare. A licensed clinician reviews the symptoms and your history in a short online consultation.
- Confirm the strength. Check the prescribed daily dose against the strength you are ordering so the tablet count works out.
- Upload the prescription. Delivery address and dispatch speed are chosen at the same step.
- Track the parcel. A tracking reference reaches you by email once the order leaves our facility.
Documents are verified before anything is dispatched. Any listing that skips that step is one to leave alone, since a pharmacy counter would refuse the same sale. Ordering ahead makes sense for a condition that has flared before. A first course is different, because the strength often changes once the response is known.
Medrol Tablet Strengths From 4 mg to 32 mg
Tablets come in 2, 4, 8, 16 and 32 mg. Approved daily doses run from 4 mg up to 48 mg. The condition sets that figure. Full details sit in the prescribing information for Medrol tablets. Each strength answers to a different job:
4 mg
The pack unit
Builds every step of the six-day course. Small enough to taper by removing one tablet at a time.
8 mg
Daily control
Holds a settled condition steady over weeks. Often the rung a higher dose lands on while stepping down.
16 mg
Active flare
Covers inflammation that has broken through. Two of these match the opening day of a Dosepak.
32 mg
Heavy suppression
Reserved for inflammation threatening an organ or sight. Short by design and reduced quickly.
Strength changes the number of tablets rather than the medication itself. A 32 mg daily dose is one large tablet or eight small ones, and the effect is identical. Higher strengths simply spare people from swallowing a handful every morning.
Splitting tablets brings its own problems. Scored tablets break unevenly and a broken half is hard to keep. Ordering the strength that matches the prescription is the cleaner route. That holds for anyone who decides to buy Medrol online.
Optic Neuritis and the Oral High-Dose Option
Optic neuritis is swelling of the nerve that carries sight from the eye to the brain. Vision in one eye goes dim or washed out over hours, and colors lose their depth. Moving the eye hurts. The Academy of Ophthalmology description of optic neuritis covers how it is diagnosed. Steroids speed the recovery up by weeks without changing where sight settles months later.
Treatment traditionally meant a drip in a hospital chair for three days. High-dose methylprednisolone by mouth was then tested against the same dose given into a vein. Patients in that trial were treated for multiple sclerosis relapses. The tablets matched the drip for recovery at one month.
Doses in that trial sat far above anything on a printed card. Patients in the oral arm swallowed 1000 mg a day, which is around 30 tablets of the strongest strength made. A Dosepak opens at 24 mg. Both carry the same active ingredient and nothing else about them matches.
Ordinary oral doses were tested here too, with a result that still guides practice. Patients given a standard steroid dose by mouth alone had more repeat attacks than those given nothing. The rates ran at 27 percent against 15. A six-day pack is not a treatment for a nerve that has just lost vision.
Corticosteroids raise pressure inside the eye in some people, and the rise produces no symptom at all. Six days rarely causes trouble, though anyone already treated for glaucoma should say so before the first tablet.
Side Effects Most People Notice by Day Two
Sleep and mood go first. A wired feeling at midnight is the classic one. A sharper appetite and a shorter fuse come with it. None of that says whether the treatment is working. Almost all of it clears within a few days of the final tablet.
| Effect | When it shows | What helps |
|---|---|---|
| Broken sleep | First or second night | Moving the later tablets earlier in the day |
| Flushed face and warmth | Days one to three | Nothing needed as it fades with the dose |
| Appetite and puffiness | Across the whole course | Less added salt for the week |
| Irritability or a high mood | Days one to three | A warning to the people around you |
| Blood sugar climbing | Within 24 hours | Closer testing in diabetes |
| Infection spreading quietly | Any point in the course | Reporting fever without delay |
How long the effects last is the question that follows. Sleep usually returns within two or three nights of the last tablet. Appetite and fluid take about a week to settle. Mood tracks the dose closely, so day five already feels calmer than day one.
Infection needs a closer look than its place on that table suggests. Corticosteroids blunt fever and pain, which are the signals that normally raise an alarm. An infection can therefore be further along than it feels. Chickenpox and shingles matter most in anyone who has never had them.
Mood swings vary more than anything else on the list. Some people feel unusually capable for three days while others turn tearful over nothing. A small number react far more strongly than that. Whatever happened last time predicts the next course well, which is better said before a repeat than after.
Who Should Wait Before Starting a Course
An untreated infection is the clearest reason to hold off. Corticosteroids lower the defenses that are fighting it. A chest infection or an abscess can then spread. The treatment was meant to help something else entirely. A fungal infection running through the body rules the tablets out entirely.
Eye infections come with their own warning. Herpes simplex on the surface of the eye gets worse under steroid treatment, and the damage can reach the cornea. Any red painful eye needs a look before a course starts rather than after it.
Diabetes rarely blocks treatment but always changes it. Glucose can climb within a day of the first tablets. Readings that were stable for years stop meaning much. Anyone using insulin should expect to need more of it while the course runs.
Several other situations shift the balance without closing the door. A stomach ulcer, uncontrolled blood pressure and recent gut surgery all belong there. So does a severe reaction to steroids in the past. Pregnancy is handled case by case, since a short course often beats an untreated asthma attack.
Age changes the calculation at both ends. Children on repeated courses grow more slowly, so their prescriptions stay as short as the condition allows. Older adults arrive with thinner bone and a higher chance of a sugar problem nobody has found yet.
Recent vaccination is the one people forget to mention. A live vaccine given days before a steroid course is the awkward combination, and travel clinics are where it usually surfaces. Both appointments tend to be arranged at short notice.
Medications That Clash With Methylprednisolone
One liver enzyme does most of the work of clearing methylprednisolone from the blood. Anything that slows that enzyme leaves more of the medication circulating, and anything that speeds it up leaves less. The dose on the card stays the same while the amount reaching the tissues does not.
These combinations are the ones that come up most:
- Clarithromycin and similar antibiotics push steroid levels up sharply
- Antifungal tablets ending in azole do the same thing
- Rifampin and several epilepsy medications weaken the dose instead
- Anti-inflammatory painkillers raise the risk of a stomach ulcer
- Warfarin becomes less predictable and needs closer blood testing
- Insulin and diabetes tablets often need adjusting upward for the week
- Water pills can pull potassium down further than either would alone
Live vaccines follow a rule with numbers attached. Treatment counts as immunosuppressive at 20 mg a day for fourteen days or longer. The CDC guidance on altered immunocompetence sets that threshold out. A six-day pack falls short of it on duration, which is why a Dosepak and a flu shot rarely collide.
Length of treatment decides most of these questions. A single short course tolerates combinations that a three-month prescription would not. That is the practical difference between a pack picked up for a flare and treatment measured in months.
What to Avoid While a Medrol Course Runs
Alcohol is the first thing to drop for the week. Alcohol works on the stomach lining from the same side as a corticosteroid, so the two together do more damage than either alone. Blood sugar gets pulled in unhelpful directions on the same day.
Grapefruit juice works on the enzyme instead. It blocks the enzyme that clears methylprednisolone, so a glass at breakfast raises the dose that actually lands. Other citrus does nothing of the kind.
Ibuprofen, naproxen and prescription diclofenac are best paused where the pain allows it. Both thin the protective layer in the stomach that steroids are already working against. Acetaminophen carries none of that risk.
Salt shows itself within a few days. Corticosteroids make the body hold on to sodium and the water that follows. That shows up as puffy ankles by day three. Cutting back on processed food for six days keeps most of that away.
This article is intended for general information and does not replace individual medical advice. Discuss dosing, side effects and repeat courses with a licensed clinician who knows your medical history.