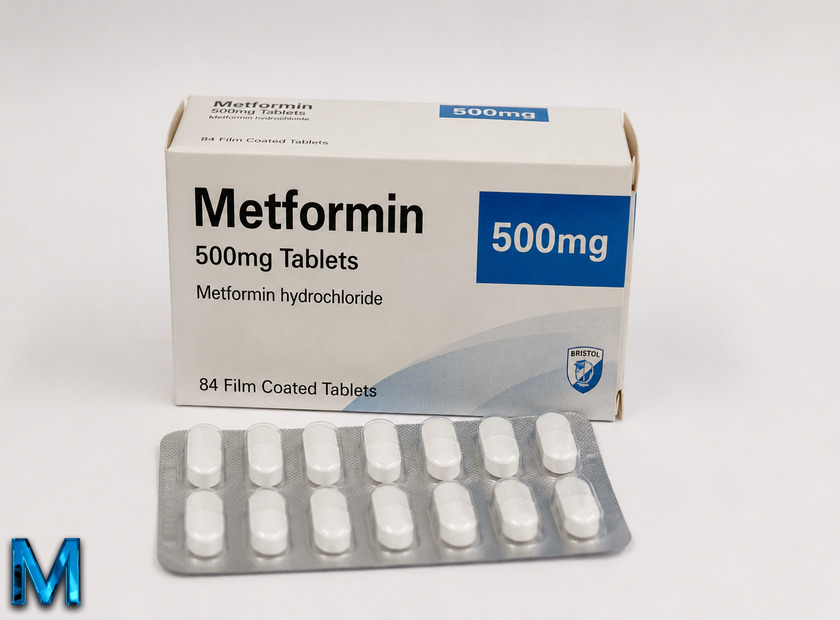
Buy metformin online — the biguanide tablet that steadies blood sugar in type 2 diabetes and eases the strain on a retina that is already at risk. Few medications in the country are dispensed as often, and fewer still are kept for as long. Most people who start it are still taking it years later. That long horizon changes what matters about the tablet. A single good reading counts for less than whether the stomach still tolerates it at week three. Dose, form and pack size all follow from that one question.
What this page covers
Why Metformin Still Leads Type 2 Diabetes Care
Guidelines still name it first for most newly diagnosed adults. Three qualities keep it there. It pulls A1c down by one to one and a half points. It rarely drives blood sugar too low on its own. And a year of tablets costs less than a month of most newer classes. Anyone about to buy metformin online is usually filling a first prescription. Few arrive here because something else failed.
The mechanism sits in the liver. Between meals a healthy liver releases stored glucose in a slow trickle. In type 2 diabetes that trickle becomes a stream. Morning readings climb before breakfast is even eaten. Metformin turns the tap down. It activates an enzyme called AMPK, the sensor cells rely on when energy runs short. Glucose production falls in response. The effect is strongest overnight, which is precisely when an untreated liver does most of its unwanted work.
Two smaller effects run alongside. The intestine absorbs less glucose from a meal. Muscle takes up more of what does arrive, and that is where insulin resistance loosens its grip. None of this asks the pancreas for extra insulin. That single fact separates metformin from the sulfonylureas that came before it. Hypoglycemia stays uncommon unless another medication is stacked on top. Weight tends to hold steady on it too, where the older tablets that squeezed the pancreas often pushed it up.
Kidney function sets the boundary. The tablet leaves the body unchanged through the kidneys. Filtration rate therefore decides two things at once. Whether it can be used at all, and how high the dose may go. Bloodwork before the first prescription is routine for that reason. The MedlinePlus monograph lists the same checks beside the full label detail.
Glucophage and the Generic That Took Over
Glucophage is the original rather than a rival. Bristol-Myers Squibb held the American patent. Once it expired, generic metformin took nearly the whole market. Plain metformin hydrochloride now fills the overwhelming majority of prescriptions written in the country.
The brand still carries weight. Glucophage is the manufacturing record every generic was measured against. Some patients happily pay for that provenance, and the reasoning is sound. Bioequivalence rules make the two interchangeable on paper. Blood sugar rarely notices a switch in practice. Some pharmacies stock several generic manufacturers at once, and tablets can differ in size or coating between them. Price is where the generic wins outright.
Extended-release versions kept separate names. Glucophage XR, Fortamet and Glumetza all carry the same molecule. Only the delivery shell wrapped around it differs.
What Metformin Changes for the Diabetic Retina
Metformin treats no eye condition directly. It starves one instead. Diabetic retinopathy is damage to the small vessels feeding the retina. Years of raised glucose is what wears those vessels down. Lowering the average is the only move that slows the process at its source. The American Academy of Ophthalmology says as much in its guidance on diabetic retinopathy. Good sugar control can sometimes return a measure of lost vision.
Retinopathy announces nothing early. Vessels leak, close off and reroute for years while sight still passes a driving test. By the time reading turns difficult, the damage sits in the macula. Options narrow sharply at that stage. Type 2 diabetes is often silent for years before anyone names it. A dilated exam therefore belongs at the start of treatment, not a year into it. Anyone given the diagnosis should book that first appointment within weeks rather than wait for something to go wrong with their sight.
Macular edema steals central vision fastest. Fluid seeps from damaged vessels into the middle of the retina and the layers swell. An OCT scan measures that swelling in microns. It is the same imaging used to track hydroxychloroquine damage on Plaquenil, run here for a different purpose. Steady glucose keeps the fluid from gathering in the first place. Injections into the eye can dry a swollen macula out later, though nothing brings back vessels that have already closed.
Whether metformin protects the retina beyond its effect on sugar stays an open question. AMPK activation dampens inflammation. Several observational analyses hint at lower retinopathy rates than glucose control alone would predict. The signal is interesting and unproven. No ophthalmologist prescribes metformin for the eye itself. Anyone weighing whether to buy metformin online for diabetes can read a retinal benefit as a bonus rather than a reason.
How Much Weight Metformin Actually Takes Off
A few pounds over six to twelve months is the honest figure. Some people lose nothing measurable at all. The largest drops land with patients who began with heavy insulin resistance. Even there the scale moves slowly. Anyone expecting the arc of a purpose-built weight medication will be disappointed by month two.
The best evidence came from a study that was not about weight. The National Institutes of Health ran the Diabetes Prevention Program across thousands of adults with prediabetes. Metformin cut the chance of progressing by 31 percent. Diet and exercise cut it by 58. Fifteen years on, the metformin group still held an 18 percent delay. A real result, and still the smaller of the two.
Several modest effects probably combine. Appetite fades a little early on. Mild nausea makes large meals unappealing, which does part of the work. Gut hormones that signal fullness appear to shift as well. Insulin sensitivity improves, and fat storage follows insulin. No single effect is dramatic. That is precisely why the total stays small.
Searches for metformin dosage for weight loss chase a number that does not exist. Prescribers set the dose against blood sugar and tolerance. Never against the scale. A 500 mg start is not a gentle weight-loss dose. It is simply where nearly everyone begins. Weight also plateaus after several months as the body settles at a steady dose. That plateau is not a sign the tablet has stopped working. Stopping treatment tends to return the weight within a few months, which is another reason it makes a poor standalone slimming plan.
Buy Metformin Online and Skip the Pharmacy Run
Pack size moves the price more than anything else here. Metformin runs daily for years, so the arithmetic differs from a week of antibiotics. A 360-tablet pack brings the cost down to $0.26 per pill. The same strength in a 90-tablet pack works out at $0.37. A US pharmacy will ask for a valid prescription before dispatch. A site that skips that step should not get the order. Patients who buy metformin online tend to order in months rather than weeks.
Choosing a pack takes one piece of arithmetic. Two 500 mg tablets a day comes to about sixty a month. So 180 tablets covers a quarter of a year and 360 covers half. Someone titrated up to three 850 mg tablets daily burns through 360 in four months. Buying past the next kidney check has little value. The dose may well change at that visit. Expiry dates matter on the largest packs, since tablets bought a year ahead still have to be usable at the last strip.
Insurance often beats every online figure outright. Generic metformin sits on the lowest copay tier of nearly every formulary. Cash payers see the opposite picture. There the metformin price per month is where large packs earn their keep. Two 360-tablet packs cover a year at two tablets a day and land near $190, so metformin cost is rarely what ends a course. Brand Glucophage stays several times higher at identical strength.
Metformin Over the Counter Does Not Exist in the US
Federal law makes it prescription-only, and no pharmacist holds discretion over that. So the search for where can i buy metformin over the counter has one accurate answer. Nowhere inside the country, however routine daily dosing starts to feel after a decade of it.
Can you buy metformin over the counter abroad? Several overseas sellers advertise exactly that. A share of what they ship has never been tested for content or purity. Counterfeit tablets are the obvious hazard. Mislabeled strength is the quieter one. An 850 mg tablet sold as 500 mg produces stomach upset that looks like ordinary intolerance. A price far below what a real supply chain could sustain rounds out the list, and it is the easiest sign to talk yourself out of.
Two signals separate a legitimate pharmacy from the rest. It asks for a prescription before taking payment. And it publishes a verifiable US address alongside a pharmacist contact. A metformin buy online request that clears both checks is the low-risk version of the same purchase. It is also how most people buy metformin online without gambling on the source.
Blurred Vision When Blood Sugar Starts to Shift
Blurring in the first weeks is usually the lens, not the tablet. Glucose moves freely into the lens and water follows it. The lens swells slightly while sugar runs high. Bring the average down and it shrinks back toward its normal shape. Focus shifts along with it. That is why print can look soft once treatment begins.
The effect is temporary and self-correcting. Vision generally settles a few weeks after the dose stops changing. Nothing needs doing beyond waiting it out. The change also runs both ways. Uncontrolled sugar blurs distance vision, and correcting it can briefly blur reading instead. Neither the immediate-release nor the extended-release form changes this pattern, because the lens reacts to glucose rather than to the tablet.
New glasses ordered inside that window are money wasted. The AAO advises waiting until readings hold steady for about a week before any refraction. A prescription measured on a moving target will be wrong by the time the lenses arrive. Anyone booked for cataract surgery has a stronger reason to wait. Surgeons prefer to take the measurements that set implant power once sugar has settled.
Vision changes that are not adaptation
- A sudden shower of floaters or dark specks drifting across one eye
- A curtain or shadow moving in from the edge of the field
- Straight lines that bend or a blank patch sitting in the center of vision
- Vision that drops in one eye over hours rather than softening in both
- Blurring that arrives months into stable treatment instead of at the start
Each of those points toward bleeding, swelling or detachment. None of them is a lens finding its shape again. They need an examination within days, not at the next annual visit. The distinction matters because both versions open with blur. Only the timing and the extra symptoms tell them apart.
Cataracts That Arrive Early in Diabetes
Diabetes moves cataract forward by years. The AAO notes in its overview of cataracts that they develop faster in younger people and in patients with diabetes. Surgery in the fifties rather than the seventies is a common pattern. The lens is often denser than the age alone would suggest.
Sorbitol explains the mechanism. Excess glucose inside the lens converts into a sugar alcohol that cannot easily leave. It accumulates and draws in water. The ordered protein lattice that keeps the lens clear then breaks up. Cloudiness follows. Less circulating glucose means less sorbitol formed, and that is the whole of metformin’s contribution here.
Two patterns dominate. Posterior subcapsular cataract clouds the back of the lens and blurs reading vision early. The rare snowflake form appears in young patients with type 1 diabetes and badly controlled sugar. That one can thicken over weeks instead of years.
Surgery itself goes well in diabetic eyes, with one caveat. A retina already inflamed is likelier to swell afterwards. Macular edema after a technically perfect operation is the main reason vision disappoints. Surgeons check recent A1c results before scheduling for exactly that reason. A well-controlled patient and a poorly controlled one face genuinely different odds. Control after the operation counts as much as control before it, since the retina keeps responding to whatever the running average has been.
The eyelids get checked at the same visit. Diabetes makes that check matter more. Meibomian gland dysfunction and chronic blepharitis both run higher in type 2 diabetes. An inflamed lid margin next to a fresh surgical wound is not what a surgeon wants. Lid disease found early gets treated first, sometimes with the long low-dose doxycycline courses prescribed for chronic blepharitis. The operation waits until the margin is quiet.
Metformin itself carries on through the procedure, which is done under local anesthesia rather than general. The steroids that follow deserve more attention. A course of prednisone can push blood sugar up sharply for as long as it runs. Readings stable for years often climb during those weeks. Surgeons and prescribers usually agree in advance who is watching the numbers while the drops taper.
Prediabetes PCOS and the Off-Label Prescriptions
One approval covers everything. Blood sugar control in type 2 diabetes, in adults and in children from age ten. Every other use below is off-label. Trial evidence and specialty guidelines support them rather than the label itself. That distinction rarely changes what a pharmacy dispenses. It does explain why coverage sometimes needs an appeal.
Where metformin gets prescribed
- Type 2 diabetes — the only use the FDA label actually covers
- Prediabetes — where fasting glucose or A1c sits above normal but below diagnosis
- Polycystic ovary syndrome — aimed at the insulin resistance behind irregular cycles
- After gestational diabetes — through the years when type 2 risk stays elevated
- Metabolic syndrome — the cluster of central weight, blood pressure and lipid changes
Prediabetes is the nearest neighbor to the approved use. The DPP data above is what supports it. Prescribers tend to reserve it for people whose numbers keep climbing despite genuine effort with food and activity. Adults under sixty with a high BMI saw the largest benefit in that trial. Younger patients also have more years of risk ahead of them. Family history and a fasting glucose that keeps creeping upward usually decide the timing more than any single reading does.
PCOS is the busiest off-label use by volume. Half to seventy percent of women with the syndrome carry measurable insulin resistance. That resistance drives the excess androgen behind irregular cycles, acne and thinning hair. Lower the insulin and androgen tends to follow. Ovulation returns for some women on metformin alone. Others need the addition of clomiphene under the Clomid brand, where the two act on different links in one chain.
The last two uses share a logic. Blood sugar usually normalizes after a pregnancy complicated by gestational diabetes. The risk of type 2 stays raised for a decade or more. Metformin sometimes bridges that window. Metabolic syndrome gets treated the same way, one lever pulled instead of three. Thyroid disease travels in this company often enough that a TSH check is standard. Patients who need levothyroxine for an underactive thyroid often take both tablets for years.
Titrating Metformin Slowly Enough to Stay on It
Metformin dosage starts at 500 mg once daily. It climbs in 500 mg steps every one to two weeks. Immediate-release tablets top out near 2550 mg a day, split across meals. Extended-release forms usually stop at 2000 mg once daily, with one brand licensed as far as 2500. Most people settle somewhere between 1000 and 2000 mg. Reaching that point takes four to six weeks by design.
500 mg
The universal starting point, taken with the largest meal of the day. Also the size of every step upward, which is why it stays in the cupboard after the dose doubles.
850 mg
The middle strength, usually twice daily with food. Three of them reach 2550 mg, the practical ceiling for the immediate-release form in adults.
Extended release
Released over several hours from a matrix shell, so one evening tablet replaces two or three daytime ones. The dose is still built up in the same slow steps.
Rushing the schedule is the commonest reason treatment fails. Start at a full 2000 mg and about half of patients spend the week near a bathroom. Many then abandon the tablet, convinced they cannot tolerate it. Climb to the same dose across six weeks and most barely notice the change. The destination is identical. Only the pace differs.
The safe range narrows as kidney clearance falls. Below an eGFR of 45 the maximum dose comes down. Below 30 metformin is stopped altogether, since the tablet accumulates once clearance drops. Levels are rechecked once or twice a year in stable patients. Pediatric prescribing follows the same slow titration on the immediate-release form. Extended-release has no established safety record below seventeen. Combination tablets pairing metformin with a newer agent exist as well, and they follow exactly the same kidney rules as the plain version. Label detail for every manufacturer sits in the DailyMed listings.
Best Time to Take Metformin With Meals
The best time to take metformin is with food, and the plate matters more than the clock. Immediate-release tablets go with breakfast and dinner. An empty stomach is where nausea and cramping hit hardest. Extended-release belongs with the evening meal. Its slow release then lines up with the liver’s overnight glucose output, the same output behind high morning readings.
Splitting or crushing an extended-release tablet destroys the mechanism. The full dose lands at once instead. An empty shell sometimes appears intact in the stool, which alarms people unnecessarily. Absorption has already happened by that point. Only the scaffold passes through.
Extended-Release Metformin and Who It Suits
Two groups benefit most from the slower form. People whose stomachs never settled on immediate-release often tolerate the same daily total when it arrives gradually. Anyone already juggling several daily medications finds one evening tablet easier to sustain than three timed around meals.
The immediate-release form keeps its own advantages. It costs less. It comes in more pack sizes. And it can be adjusted in smaller steps while the dose is still being tuned. Switching between the two is straightforward at an equivalent daily total. The rhythm of the day changes completely, though. Cost barely separates the two at generic prices, so tolerance decides the choice far more often than the invoice does.
Diarrhea and the Side Effects That Settle Down
Digestive complaints dominate the list, and they arrive early. A third to a half of patients notice loose stools, nausea or cramping within the opening two weeks. For most it fades within two to four weeks as the gut adapts. Taking every dose with a full meal is what shortens that stretch. Moving to the extended-release form is the usual next step when loose stools outlast the first month.
Vitamin B12 is the one worth tracking over the long run. Metformin interferes with absorption in the lower intestine. After several years a measurable share of patients drift low. Depletion shows up as fatigue and as tingling in the hands and feet. Rarely it reaches the optic nerve. That kind of vision loss is subtle and painless. It is also easy to mistake for a lens problem in someone who already has diabetes. An annual blood test beside the usual kidney panel settles the question cheaply.
Alcohol deserves a direct answer rather than a hedge. Heavy or binge drinking raises the risk of lactic acidosis. The label names that rare buildup of acid explicitly. A glass with dinner is a different proposition from an evening of drinking on an empty stomach. Liver disease or reduced kidney function turns the guidance into a hard limit.
A few situations call for a short pause instead. Severe vomiting, prolonged diarrhea or a fever that stops fluids going down all concentrate the medication. The same caution applies around contrast imaging and general anesthesia. Both are arranged in advance. Resuming afterwards is routine once kidney function has been confirmed.
The A1c Number That Shows Metformin Is Working
A1c delivers the verdict, and it takes about three months. The test reflects average blood sugar across the lifespan of a red blood cell. Checking sooner measures a stretch when the dose was still climbing. Most adults with type 2 diabetes aim below 7 percent. Older patients and those with heart disease are often given a looser target on purpose.
Fasting readings move first. Morning glucose usually drops within one to two weeks of a stable dose. That is the earliest sign liver output has come down. Energy follows within a month or so. Patients often describe an afternoon slump lifting, something they had stopped registering as a symptom at all. Home meters pick the change up well before any laboratory test does, which is why prescribers ask for a log across the opening weeks.
Falling short of target is not a failure of the medication. Type 2 diabetes progresses on its own schedule. After several years many people need a second agent for reasons unrelated to adherence. Metformin almost always stays in the regimen when that happens. Newer classes were tested as additions to it, not as replacements. Repeat supplies are the simplest part of long-term care, and most people who buy metformin online are doing exactly that, one refill at a time.
One appointment belongs in the same rhythm as the bloodwork. A dilated eye exam every year tracks what A1c cannot show directly. It reveals whether the retinal vessels are holding up under the average that A1c reports. Good numbers and a clean retinal scan together are what long-term control actually looks like.
Disclaimer
This page is general education, not personal medical advice. Dosing, eye screening intervals and treatment decisions belong with a licensed provider who knows your full history. Speak with a qualified professional before starting or stopping any medication.