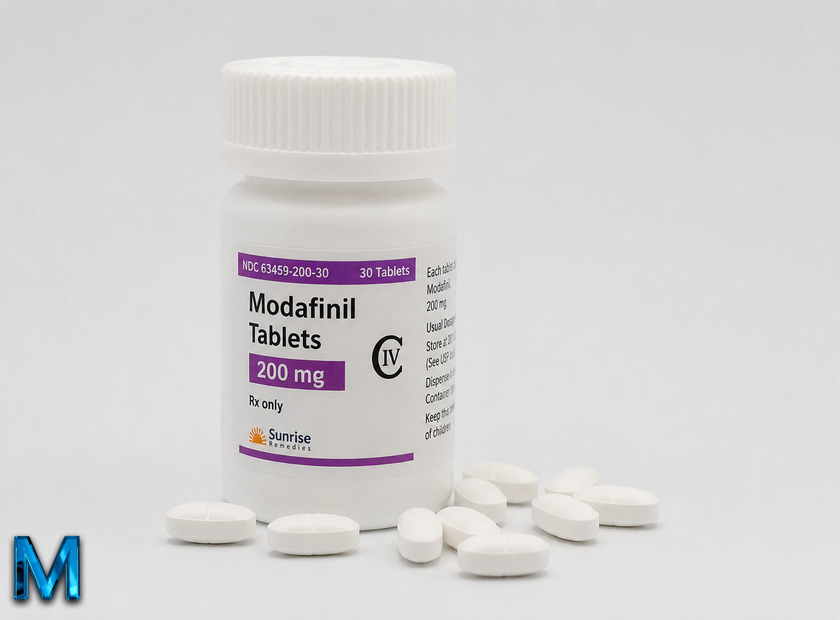
Buy modafinil online — the once-daily wakefulness tablet that steadies the day when narcolepsy sleep apnea or night shifts break the sleep-wake cycle. Three conditions carry an FDA approval, and all three share one symptom. The body stops delivering usable wakefulness on schedule. Modafinil does not manufacture energy to replace it. It raises the floor under alertness so the day becomes workable again.
How Modafinil Turns Down Daytime Sleepiness
Wakefulness gets promoted rather than forced. That distinction runs through everything else on this page. People who buy modafinil online are usually fighting a pressure to fall asleep. It arrives without permission during meetings, drives and long afternoons. The tablet lowers that pressure. It does not stack excitement on top of a tired brain.
Mechanism explains the difference. Modafinil binds the dopamine transporter weakly and blocks reuptake. Dopamine signaling then nudges upward in the regions governing arousal. Orexin and histamine pathways in the hypothalamus respond downstream. Classic stimulants flood the synapse instead. That flood produces the rush, the crash and the appetite for a higher dose next week.
Onset lands somewhere between thirty and sixty minutes. Peak concentration follows around the two to four hour mark. Useful effect then holds across a working day. Half-life sits near fifteen hours in healthy adults, and that is the most practical number on the label. A tablet swallowed at noon is still circulating well after midnight.
Sleep itself stays necessary. Modafinil masks nothing about sleep debt and repays none of it. Someone sleeping five hours a night will still accumulate the deficit while feeling functional. All three approved uses involve a diagnosed sleep disorder. None of them involve a crowded calendar.
One quiet contributor gets missed constantly. Sedating antihistamines push daytime drowsiness in the opposite direction. Diphenhydramine products are the usual culprit. Fighting one medication with another rarely ends well. Removing the sedative first is the cleaner move.
Narcolepsy and the Sleep Attacks It Softens
Narcolepsy is where this medication has its firmest footing. The American Academy of Sleep Medicine recommends modafinil for adults with narcolepsy. That sits in its 2021 guideline on central disorders of hypersomnolence. Treatment usually opens at 200 mg in the morning. Because the condition is lifelong, so is the prescription in most cases. That is also why patients with narcolepsy who buy modafinil online tend to order by the quarter.
The underlying problem is a shortage, not a malfunction. Orexin-producing neurons in the hypothalamus die off. Orexin is the signal holding the waking state stable. Without enough of it, the boundary between sleep and wakefulness gets porous. Sleep intrudes on the day. Wakefulness fragments the night.
Sleep attacks are the symptom people describe first. An overwhelming urge to sleep arrives within minutes and does not negotiate. Modafinil widens the gap between those episodes and shortens them. Full normal alertness is not the realistic target. Most patients describe the result as a day they can plan around.
Cataplexy sits outside its reach entirely. Sudden muscle weakness triggered by laughter belongs to narcolepsy type 1. Wakefulness medication does nothing for it. A second prescription usually handles that piece. Splitting the daily dose is another common adjustment. Part goes in the morning and part at midday. Patients whose afternoons collapse benefit most from it.
Diagnosis carries one caution. Persistent sleepiness is not proof of narcolepsy, and an underactive thyroid produces a strikingly similar picture. A thyroid panel belongs in the workup before any wakefulness medication starts. Levothyroxine replacement resolves that version of the complaint on its own.
Sleep Apnea and the Sleepiness CPAP Leaves Behind
Approval in obstructive sleep apnea comes with a condition attached. Modafinil is cleared for residual excessive sleepiness in patients already treated for the airway obstruction itself. CPAP stays first, and the tablet enters only when sleepiness outlasts consistent use of the machine.
Night-time mechanics explain it. The upper airway collapses repeatedly during sleep and oxygen dips. Each time, the brain surfaces briefly to reopen it. Most people never remember these arousals. Deep sleep gets shredded anyway, dozens of times per hour. Morning then arrives with the body technically rested and the brain nowhere near it.
CPAP fixes the mechanics for the large majority. Breathing steadies, oxygen holds, and sleep architecture reassembles over weeks. A meaningful minority never gets that dividend. Their apnea readings normalize while daytime function stays stuck. That gap is what modafinil was studied for.
Evidence behind the indication comes from a twelve-week randomized trial. Black and Hirshkowitz enrolled patients on nasal CPAP who stayed sleepy. Results appeared in Sleep in 2005. Modafinil beat placebo on both subjective and objective sleepiness measures. Adherence to CPAP held steady during treatment, which mattered as much as the primary result.
Several things get checked before a prescription makes sense:
- CPAP pressure is properly titrated and the mask actually seals through the night
- Usage data shows real adherence, not three hours on good nights
- Total sleep time is adequate, since seven hours in bed cannot produce eight hours of sleep
- Anemia, depression and low iron have been ruled out as separate causes
- Sedating medications taken in the evening are reviewed and adjusted where possible
Weight underlies much of this for many patients. Obesity drives both apnea severity and insulin resistance. Plenty of people therefore carry a sleep study and a metformin prescription together. Neither condition improves the other. Treating one usually makes the other easier to control.
Why Modafinil Never Replaces CPAP at Night
Feeling awake and being treated are two separate things. A tablet does nothing to the airway. Every collapse still happens and every oxygen dip still registers, so cardiovascular strain carries on unchanged. What disappears is the warning signal.
That trade is worse than it sounds. Daytime sleepiness is often the only symptom that prompts a sleep study. Remove it pharmacologically and the underlying condition goes quiet without going away. Untreated apnea carries links to hypertension, arrhythmia, stroke and metabolic disease.
Two problems, two tools. Sleep physicians treat them as complements with fixed roles. The machine handles the night. The tablet handles what the night leaves behind. Reversing that order removes the part of treatment that protects the heart and brain.
Night Shifts Against the Body Clock
Shift work disorder is the third approved use, and the dosing rule changes here. Modafinil goes in roughly one hour before the shift starts, which takes morning dosing off the table. Peak effect then lands during the hours that matter. Off days generally do not call for a tablet at all.
Nothing broken in the brain of a night worker. The conflict is between a schedule and a circadian clock that keeps insisting on daylight. Core body temperature drops in the small hours regardless of what the roster says. Alertness bottoms out with it. Melatonin release peaks while a nurse or a driver most needs to be sharp.
Rotating rosters make it worse than permanent nights. The internal clock never settles anywhere, so each rotation restarts an adjustment that takes days. Sleep after a shift then arrives in short broken blocks in a bright bedroom. Total sleep debt builds week over week.
Modafinil supports the working hours and stops there. Circadian timing stays untouched, so the underlying misalignment is still present on the drive home. Fifteen hours of half-life also has consequences for daytime sleep. A tablet taken at ten at night is still active at one in the afternoon, which is exactly when a night worker is trying to sleep.
Practical scheduling does much of the work here. Bright light during the first half of a shift helps. So do dark glasses on the commute home and a blacked-out bedroom. Anyone leaving night work behind tends to recover without long-term medication. That separates this indication from narcolepsy sharply.
Buy Modafinil Online and What a Month Costs
Price per tablet is the number to compare when you buy modafinil online, and it moves a long way with quantity. The 200 mg strength opens at $1.76 per pill and settles at $0.88 on the largest pack. The 100 mg tablets run from $1.64 down to $0.82. One tablet a day is the standard schedule, so pack size converts directly into months of coverage.
Each row carries two figures. The struck-through number is the standard total, and the bold one is what the order comes to.
Modafinil pricing
Generic Provigil — 100 mg and 200 mg in stock
| Package | Per pill | Daily use covers | You save | Per pack |
|---|---|---|---|---|
| 200 mg tablets | ||||
| 30 pills | $1.76 | 1 month | — | $52.80 |
| 60 pills | $1.28 | 2 months | $28.80 | $105.60$76.80 |
| 90 pills | $1.12 | 3 months | $57.60 | $158.40$100.80 |
| 180 pills | $0.96 | 6 months | $144.00 | $316.80$172.80 |
| 360 pills | $0.88 | 12 months | $316.80 | $633.60$316.80 |
| 100 mg tablets | ||||
| 30 pills | $1.64 | 1 month | — | $49.20 |
| 90 pills | $1.04 | 3 months | $53.67 | $147.60$93.93 |
| 180 pills | $0.89 | 6 months | $134.18 | $295.20$161.02 |
| 360 pills | $0.82 | 12 months | $295.20 | $590.40$295.20 |
Matching a pack to a diagnosis is more useful than chasing the lowest unit price. Narcolepsy runs indefinitely, so a six or twelve month supply matches how the condition behaves. Shift work is the opposite case. Tablets get used on working nights only, which stretches ninety pills across far more than three months. Anyone starting treatment has a reason to order small quantities while the dose is still being settled.
Modafinil cost without insurance is what puts these figures in context. Brand Provigil without insurance runs well past $1,000 for thirty tablets at most chains. Generic modafinil with a discount card typically lands between $25 and $60. Published coupon prices move week to week. Coupons apply per fill, which is where larger quantities pull ahead.
Where to buy modafinil online is a narrower question than it looks. One condition applies everywhere in the United States: a pharmacy will ask for a valid prescription before dispensing any strength, and that requirement does not soften online. Listings promising otherwise are operating outside federal law regardless of where the tablets ship from.
Is Generic Modafinil the Same as Provigil
Therapeutically equivalent is the formal answer. Generic modafinil carries an AB rating from the FDA. Same active ingredient, same strengths, and bioequivalence demonstrated against the reference product. Clinical effect is expected to match. Both versions come out of facilities held to identical manufacturing standards.
Provigil still deserves its reputation. Lafon Laboratories in France created the molecule, and Cephalon carried it through American registration. Every generic leans on the safety record built there. That history is real value, and some patients stay with the brand for the consistency of one manufacturer. Paying for it is a defensible choice, not a wasted one.
Cost is where the two part company. Generic supply reached American pharmacies in 2012, and the price gap since then has been enormous. Most prescriptions in the United States are filled with the generic for that reason alone. Asking for it by name at the counter is the simplest saving available on this medication.
What Schedule IV Means at the Pharmacy Counter
Modafinil is a Schedule IV controlled substance in the United States. That classification changes the paperwork rather than the pharmacology. Accepted medical use is established. Potential for misuse and dependence exists but sits well below Schedule II territory. What patients notice is a set of rules around refills.
Several practical limits follow from the schedule:
- A prescription expires six months after it is written, with five refills as the ceiling
- Early refills are commonly blocked, so a supply needs reordering before the last few tablets
- Transferring a prescription between pharmacies is restricted in many states
- A prescriber must hold DEA registration, which not every clinician does
- Any seller advertising no prescription requirement is breaking federal law outright
Anyone about to buy modafinil online can treat that last point as a single filter. Planning around the other four prevents most gaps in treatment. Someone on a stable narcolepsy regimen benefits from reordering two weeks ahead of the last tablet. Travel needs the same forethought, since a lapse in supply brings the original sleepiness straight back.
Modafinil Dosage and the Timing That Matters
Two hundred milligrams once daily is the approved dose for all three indications. It also functions as the practical ceiling for most patients. Trials tested 400 mg and tolerability held up, yet no consistent benefit appeared against the standard dose. Extra milligrams mostly buy extra side effects.
Starting lower has clear uses. A 100 mg opening dose suits patients sensitive to stimulant-type medication. Anxiety, raised blood pressure and slowed clearance in older adults point the same way. Severe hepatic impairment calls for roughly half the usual dose. The prescribing information on DailyMed spells that reduction out. Starting small also yields information, since insomnia or palpitations at 100 mg tell a prescriber plenty before the dose doubles.
Timing causes more trouble than dose size. A tablet taken at midday keeps working deep into the night. Insomnia on modafinil usually traces back to the clock rather than the milligrams. Moving the dose to seven in the morning resolves it in many cases. Splitting 200 mg into two halves helps patients whose afternoon slump returns early.
Food changes little. Absorption slows with a meal while total exposure stays intact, so a tablet with breakfast is a reasonable answer to nausea. Doses can be taken with or without it. Consistency of timing matters far more than consistency of meals.
Headache Nausea and Other Common Reactions
Headache tops every list, reported by roughly a third of patients in trials. Nausea comes second at around one in ten. Nervousness, insomnia and reduced appetite fill out the common tier. Most fade across the first two weeks, and a smaller dose or an earlier one settles the rest.
Blood pressure and heart rate call for monitoring, not alarm. Modest increases occur in some patients, which matters for anyone already on antihypertensive treatment. Existing arrhythmia, recent cardiac events or uncontrolled hypertension shift the risk calculation. A cardiovascular history belongs in the conversation before the first prescription.
Three categories warrant a fast response:
Stop and seek medical attention
- Rash of any kind, particularly with blistering or peeling — severe skin reactions are rare but serious. Most reported cases appeared within the first five weeks
- Mania, hallucinations, agitation or suicidal thoughts — risk runs higher with a history of psychosis or bipolar disorder
- Chest pain, breathlessness or an irregular heartbeat — these need assessment, not a dose adjustment
The MedlinePlus page for modafinil sets out the full list in plain language. Dependence potential exists on paper and stays low in practice at approved doses. Abrupt discontinuation after long use brings the original sleepiness back. A withdrawal syndrome is not what follows.
Interactions Worth Checking Before the First Dose
Hormonal contraception is the interaction that catches most people out. Modafinil induces the CYP3A4 enzyme, which speeds the breakdown of estrogen-based contraceptives and lowers their reliability. Pills, patches, rings, implants and hormonal coils are all affected. An additional method is needed during treatment and for a full month afterward.
Enzyme effects run in both directions, and that is what makes the interaction profile awkward. CYP3A4 gets induced while CYP2C19 gets inhibited. Medications cleared by the first route may lose potency, and cyclosporine is the documented case: blood levels fell by half in patients on 200 mg daily. Medications cleared by the second may accumulate instead. Warfarin sits apart from both on CYP2C9, where the label still asks for tighter monitoring of clotting times.
Proton pump inhibitors sit in that second group. Omeprazole depends heavily on CYP2C19 for clearance. Anyone taking omeprazole for reflux alongside modafinil may see higher exposure than expected. The combination is not forbidden. It belongs on the medication list a prescriber sees, not in a cupboard nobody mentions.
Thyroid treatment needs a separate note for a different reason. Sleepiness that persists on a stable modafinil dose sometimes reflects an undertreated thyroid. Revisiting levothyroxine dosing comes before raising the wakefulness dose. Two medications aimed at the same symptom rarely need to be stacked.
Caffeine is the interaction people manage themselves. Both substances raise alertness through different routes, and the combined effect on tremor, anxiety and evening sleep is predictable. Cutting habitual coffee intake for the first two weeks makes the medication easier to judge on its own terms.
Why Eye Doctors Ask About Your Snoring
Sleep apnea shows up in an eye examination more often than patients expect, and the eyelids are usually where it surfaces first. Several ocular conditions cluster around untreated apnea. A systematic review of forty-nine studies pooled the numbers. Odds ran 3.68 for floppy eyelid syndrome and 3.98 for non-arteritic anterior ischemic optic neuropathy. Glaucoma came in at 1.49. The analysis appeared in Graefe’s Archive for Clinical and Experimental Ophthalmology.
Floppy eyelid syndrome is the most telling of the three. Upper eyelids become rubbery and lax enough to turn outward during sleep, usually worse on the side a person lies on. Morning symptoms follow a pattern: sticky discharge, redness, watering and irritation that settles as the day goes on. The American Academy of Ophthalmology notes that most patients with floppy eyelids turn out to have sleep apnea. That makes the eyelid finding a real screening opportunity.
Optic nerve involvement is the more serious end. Non-arteritic anterior ischemic optic neuropathy causes painless vision loss in one eye, and patients characteristically notice it on waking. Overnight oxygen dips and blood pressure swings are the suspected mechanism. Anyone who has had one episode has reason to be assessed for apnea, because the fellow eye carries ongoing risk.
Glaucoma rounds out the group with a smaller but consistent association. Repeated hypoxia appears to affect optic nerve head perfusion, and severity tends to track the number of apnea events per hour. Pressure-lowering treatment with bimatoprost drops or latanoprost drops addresses the eye alone. Untreated apnea keeps working against it every night.
Modafinil belongs nowhere in this part of the story. It treats the daytime symptom of apnea. Eyelid laxity, optic nerve perfusion and intraocular pressure stay untouched. That separation is why the screening question exists. An eye finding can be the first clue that a sleep study is overdue.
Air Leaks From a CPAP Mask and Dry Eyes
A poorly sealed mask sends a thin stream of air upward across the eye all night. Tear film evaporates under it. Waking with gritty burning eyes after a night on CPAP is mechanical rather than medical. It is also one of the quieter reasons people abandon the machine.
Fit solves most of it. A cushion sitting too high aims the leak straight at the eye. Uneven straps and an oversized mask do the same. Adding humidification to the circuit helps separately. Sleeping on the back, not pressed into a pillow, reduces the sideways leak.
Other contributors stack on top of that. Antihistamines thin the tear film, and so does isotretinoin treatment through its effect on the meibomian glands. Someone using CPAP while taking either one has two separate reasons for a dry ocular surface. Raise both at an eye appointment before drops become the default answer.
Disclaimer
This page provides general information about a prescription medication and does not replace personal medical advice. Talk to your doctor or pharmacist before starting, stopping or changing any treatment. That applies to anyone using hormonal contraception or being treated for a diagnosed sleep disorder.