Buy Plaquenil online — the hydroxychloroquine tablet behind steadier lupus and arthritis control and the eye checks that now run on OCT imaging. It calms an overactive immune system without switching it off. The one real cost lands in the retina. That is why an eye clinic has something to say about a rheumatology tablet.
Published August 2026 · screening intervals on this page follow the 2025 revision from the American Academy of Ophthalmology
On this page
Eleven answers before your next refill
01Uses in lupus and rheumatoid arthritis
02Why dosage follows body weight
03The eye exam now runs on OCT
04Immunosuppressant or steroid
05Prices and what a year costs
08How rare retinal toxicity really is
Plaquenil Uses in Lupus and Rheumatoid Arthritis
Plaquenil carries four approved uses in the United States. It treats systemic lupus erythematosus, and also discoid lupus, the rash-dominant form that stays in the skin. Autoimmune conditions rarely travel alone. Thyroid disease sits alongside lupus and rheumatoid arthritis often enough to be checked. Levothyroxine is the usual replacement once the gland slows. Rheumatoid arthritis in adults sits on the same label. And Plaquenil still does its original job from 1955, which is malaria.
Lupus is where it matters most. Nearly every person with systemic lupus is offered hydroxychloroquine. Most stay on it for life. The reason goes well past symptom relief. Long-term use lowers flare frequency. It protects the kidneys. Clot risk falls. Survival improves. Few medications in rheumatology can claim all four benefits at once, which is why Plaquenil outlasts almost everything else on the prescription list. People who buy Plaquenil online are usually filling a script they expect to keep for a decade.
Rheumatoid arthritis uses it differently, and here it suits mild disease best. It also sits alongside methotrexate in what rheumatologists call triple therapy. Joint swelling settles and morning stiffness shortens. Plaquenil adds almost no monitoring burden of its own.
The malaria work continues quietly. Travelers take it weekly before a trip, during the stay and for weeks after returning home. That only applies where the parasite remains sensitive, and resistance has narrowed the map considerably. Nothing about that schedule resembles the rheumatology one.
Off-label use is wide and well established:
- Sjögren’s syndrome — for fatigue, joint pain and dryness, including dry eye
- Antiphospholipid syndrome — added for its mild anticlotting effect
- Cutaneous lupus and lichen planus — rash-dominant disease without organ involvement
- Juvenile idiopathic arthritis — in selected children under specialist care
The mechanism explains that breadth. Hydroxychloroquine slips into lysosomes, the small acidic compartments inside cells. Once there it raises the pH. Antigen processing slows down and toll-like receptor signaling quiets. The immune system keeps fighting infection but stops shouting at the body’s own tissue. That narrow kind of restraint is unusual, and it explains why infection risk barely moves. A plain summary of approved use sits at the American College of Rheumatology.
A short list of people should not start Plaquenil at all. Anyone with existing macular disease belongs at the top, because damage from the medication would be difficult to separate from damage already there. Known allergy to the antimalarial family rules it out as well. Porphyria and psoriasis sit in a grey zone where flares have been reported, so specialists weigh those cases individually rather than by rule. G6PD deficiency worries people far more than it should. That old caution came from other antimalarials, and studies of G6PD-deficient patients on standard doses have not found the hemolysis it predicted.
Why Plaquenil Dosage Follows Body Weight
Dose is capped by weight, not by diagnosis. The ceiling is 5.0 mg per kilogram of actual body weight each day. Someone at 70 kg tops out at 350 mg. Lupus and rheumatoid arthritis run the same arithmetic. The limit exists to protect the retina rather than to control disease.
That word “actual” carries history. Older prescribing used ideal body weight. Slim patients ended up dosed too high while heavy patients ended up too low. Real weight replaced it, and the 2025 review left the number untouched. Above roughly 80 kg the practical cap flattens at 400 mg per day.
Tablet strengths have quietly widened. For decades the 200 mg tablet stood alone in American pharmacies, so a 400 mg daily dose meant taking two of them. Manufacturers have since added 100 mg, 300 mg and 400 mg versions. Odd weight-based totals became much easier to hit, and nothing needs splitting anymore.
Most people start high and step down, with 400 mg daily through the first months as the common pattern. A reduction follows once the disease settles. The lowest effective dose is whatever holds symptoms while staying under the ceiling. For many that lands at 200 mg.
Kidney function shifts the target too. Hydroxychloroquine clears partly through the kidneys. Reduced filtration raises blood levels at any given dose, so prescribers often trim the daily amount when kidney disease is present. Significant liver disease calls for the same caution. The retina notices that difference over the years.
Going above the ceiling creates no single-day emergency. Risk builds with cumulative exposure instead. That is why anyone about to buy Plaquenil online should have the weight calculation settled first. A dose set correctly in year one still pays off in year twelve.
The Plaquenil Eye Exam Runs on OCT Now
In 2025 the American Academy of Ophthalmology rewrote its screening advice, and the headline change is which test now leads. Optical coherence tomography comes first, with wide-pattern fundus autofluorescence beside it. Visual fields dropped to a confirming role. A baseline examination belongs soon after the first tablet, not sometime during the first year.
That shift matters for anyone screened under the old routine. A field test alone was once treated as adequate, and it now ranks second. OCT finds thinning in the outer retina months or years earlier. A field test needs a blind spot to have formed already. Imaging does not wait for that.
The schedule after baseline is simple. Screening repeats every year while treatment continues. Skipping the annual visit during the first five years is only reasonable without risk factors. That list of risk factors grew in the same revision. The screening statement itself is posted by the Academy of Ophthalmology.
Timing the baseline early has a practical purpose. It records the retina before the medication had any chance to act. Every later scan gets measured against that image. Without it a clinician is guessing whether a thin patch is new or lifelong. Anyone planning to buy Plaquenil online should book the baseline in the same week the first pack arrives.
A flagged scan does not mean the tablet stops that afternoon. Early signals get repeated and compared before anyone acts, because artefacts and other retinal conditions can mimic the same pattern. If genuine change is confirmed, the rheumatologist and the ophthalmologist decide together, weighing how well the disease is controlled against how much retina is at stake. Sometimes the answer is a lower daily dose. Sometimes it is a different medication entirely. Either way the decision belongs to two specialists rather than to one scan.
Tests That Make Up the Screening Visit
A Plaquenil screening appointment runs about forty minutes. No needles are involved. Pupils get dilated, so someone else should drive home. Here is what the visit contains:
- Spectral-domain OCT — a light-based cross section of the retina, sensitive to the earliest outer layer thinning
- Wide-pattern autofluorescence — a photograph that makes stressed retinal cells glow brighter than healthy ones
- Automated visual field — the bowl with flashing lights, now used to confirm what imaging suggests
- Dilated fundus examination — the direct look, mainly to rule out other retinal disease
- Multifocal ERG — an electrical recording, reserved for unclear cases
One detail matters if your ancestry is East Asian. Damage in that group tends to sit further from the center. It forms a pericentral ring. A standard 10-2 field pattern can miss it entirely. Newer programs such as 24-2C cover the central and outer zones in a single run.
Is Plaquenil an Immunosuppressant or a Steroid
Neither label fits. Plaquenil is an antimalarial that behaves as a disease-modifying antirheumatic medication. That family goes by the shorthand DMARD. Hydroxychloroquine dampens an overactive immune response without suppressing immunity broadly. Infection risk barely moves on it.
The steroid question comes up constantly. Usually because both get prescribed for lupus at the same time. They are unrelated compounds. Steroids such as prednisone in autoimmune flares act within hours. They also charge a long-term price in bone, blood sugar and eye pressure. Hydroxychloroquine works over months and asks for almost nothing back. Rheumatologists often use one to taper the other.
It is no biologic either. Biologics are injected proteins aimed at single immune targets, while this one is a small molecule in tablet form that touches several pathways gently.
Nor is it a blood thinner in the usual sense. It does lower clot risk slightly, which is why antiphospholipid syndrome sits on the off-label list. Nobody prescribes it for that effect alone.
Laboratory monitoring reflects the same mildness. Methotrexate demands regular liver and blood counts. Hydroxychloroquine asks for far less. Periodic bloodwork tracks the underlying disease more than the tablet. The organ that needs watching is the retina, and it gets watched by imaging rather than by lab tests. A patient overview sits on MedlinePlus.
Buy Plaquenil Online and What a Year Supply Costs
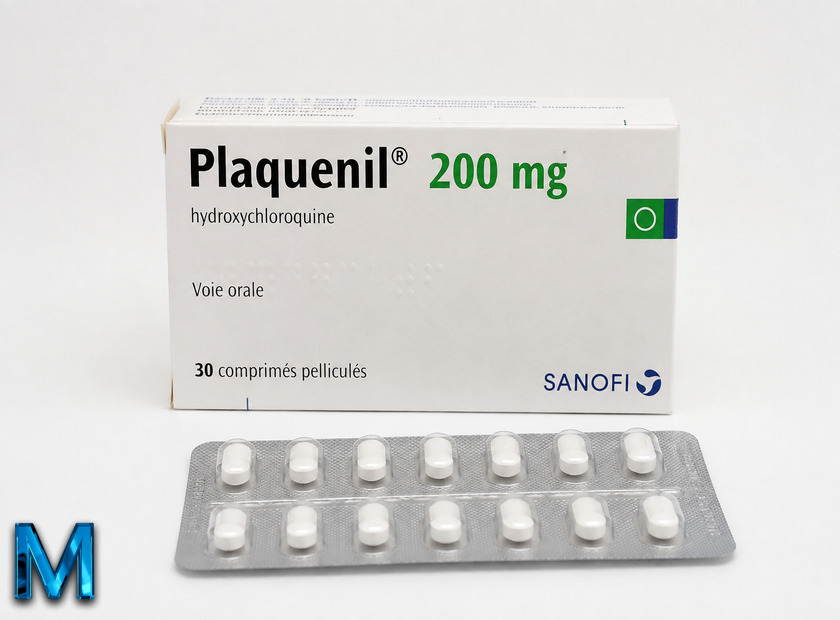
Plaquenil cost drops sharply with pack size. The drop is steeper than with most chronic medications. A thirty-tablet box of the 200 mg strength runs $2.97 per pill. The same tablet inside a 360-count pack falls to $2.40. Anyone asking how much does Plaquenil cost across a full year should price the large pack first.
Work the year out before choosing a strength. The two options are not priced the same for an identical daily dose. Take a patient on 400 mg per day. One route is two 200 mg tablets. That burns 720 tablets across twelve months and comes to roughly $1,728 at the large-pack rate. The other route is a single 400 mg tablet. That needs 360 tablets and lands near $1,465. Same medication, same milligrams, about $260 apart.
Someone holding steady on 200 mg daily needs 360 tablets for the year. That works out to $863.89. A shade under $2.40 a day.
Alternating doses complicate the count a little. A ceiling of 300 or 350 mg usually means one strength on some days and another on the rest. The annual tally then sits between the two figures above. Ordering both strengths together avoids a second shipping charge later.
Discount cards work differently than most people expect. Searches for a Plaquenil coupon mostly lead to retail savings programs. Those cards work against a prescription filled at that chain. They do nothing for a bulk pack ordered elsewhere. Comparing the card price against the per-pill figure above takes five minutes.
One more search needs a plain answer. People looking to buy Plaquenil without prescription will find that hydroxychloroquine is prescription-only across the United States. A legitimate pharmacy asks for a valid script before dispatching anything. That requirement serves a purpose. The dose has to match body weight, and nobody can run that calculation without knowing the patient.
Bulk ordering suits Plaquenil better than most medications. Treatment runs for years. The daily amount rarely changes once it is set. People who buy Plaquenil online in the largest pack are simply matching the order to how the tablet is actually used.
Generic Plaquenil and What the Brand Adds
The generic name is hydroxychloroquine sulfate. The generic tablet holds the same active molecule at the same strength. FDA approval required proof of bioequivalence, so blood levels track within a narrow band of the original. For most people the switch is invisible.
The brand still carries something copies do not. Plaquenil is the formulation the trials ran on. That covers the malaria work of the 1950s. It covers the lupus survival data of the last two decades. Seventy years of records describe that particular tablet. Depth of that kind is what people pay for, and it is a reasonable thing to want in a medication taken daily for life.
Price is where the generic answers back, and the gap widens noticeably across a year of continuous use. Both routes deliver the same milligrams to the same receptors.
One wrinkle is worth knowing about. Different manufacturers use different fillers and coatings. A minority of long-term users report that stomach tolerance shifts when the supplier changes. Nothing about the active ingredient has moved. The inactive parts have. Staying with one manufacturer spares you from wondering whether a new symptom belongs to the disease or to the box.
Large packs help here almost by accident. People who buy Plaquenil online in 360-count boxes get many months out of a single production run. Batch variation stops being a question at all.
Plaquenil Takes Weeks to Work for a Reason
Expect the first real change between one and three months. Full benefit can take six. Nothing at all happens in the first two weeks, and that silence is not a sign of failure.
The delay is built into how the molecule moves. Hydroxychloroquine has an elimination half-life near forty days. It accumulates in tissue before doing much of anything. Steady state arrives only after months of daily dosing, and blood levels climb slowly before holding for a long stretch. That same sluggishness helps later on. A single forgotten tablet barely dents a reservoir built over months.
Symptoms improve in a rough order. Fatigue and skin changes usually ease first, with joint pain following behind them. Mouth ulcers and rash can take longer still.
Higher starting doses exist for exactly this reason. Four hundred milligrams daily fills the reservoir faster, and a step down follows once the disease quiets.
Judging whether it has failed takes patience most people are not warned about. Six months of steady daily dosing is the usual point at which rheumatologists reassess, and stopping earlier than that risks abandoning something that had not finished working. Hydroxychloroquine blood level testing exists and is sometimes used when a patient reports no benefit at all, mainly because it separates a genuine non-responder from someone who has been missing tablets. Adherence turns out to explain a surprising share of apparent failures.
The Best Time of Day to Take Plaquenil
There is no pharmacological best hour. A forty-day half-life flattens any timing effect completely. What matters is food and habit. Taking the tablet with a meal cuts the nausea that troubles people early on. A glass of milk does the same job, and this matters because nausea is the single most common reason for quitting too soon.
Evening dosing is popular for a practical reason. Nausea slept through is nausea barely noticed. Splitting 400 mg into morning and evening halves spreads the stomach load. Some rheumatologists suggest that pattern from the start. A few users report vivid dreams on evening dosing and shift it earlier. Both approaches work.
Plaquenil Toxicity Stays Rare at the Right Dose
The numbers are calmer than the reputation. Stay at or below 5 mg per kilogram and retinal toxicity runs under 1 percent through five years. Through ten years it stays under 2 percent. Past twenty years the added risk each year is still below 5 percent. Most people on Plaquenil never develop a retinal problem at all.
Risk is not spread evenly. The 2025 review named several factors that lift an individual above the average. Duration and dose lead, as they always have. Kidney impairment comes next. Halving the filtration rate roughly doubles the risk, because hydroxychloroquine lingers longer. Tamoxifen taken alongside raises it sharply. That combination turns up in women managing breast cancer and an autoimmune condition at once.
Two factors were new in this revision. Starting hydroxychloroquine after age 45 carries more risk than starting young. Women appear more susceptible than men at equal exposure. Neither point changes whether Plaquenil is worth taking. Both change how closely the retina gets watched, which is the whole reason for naming them. The Lupus Foundation of America keeps a patient-facing summary of the same ground.
Cumulative exposure is the real currency here. Five years at a correct dose is safer than three years above the ceiling. That is also why the weight calculation carries more weight at the beginning of treatment than at any point after.
Why Bull’s Eye Damage Should Not Appear Anymore
Bull’s eye maculopathy is the image every article about hydroxychloroquine reaches for. A pale ring around the central retina. Visible to the naked eye through a dilated pupil. The 2025 statement says something blunt about it. With correct dosing and proper screening, it should no longer be encountered. Seeing one means the system failed somewhere upstream.
That reframing is worth sitting with. The classic sign is no longer the diagnosis. It is late evidence that damage ran unchecked for years. By the time a ring is visible, the photoreceptors that formed it are already gone. Modern screening aims about a decade earlier than that.
What imaging looks for first is subtle. Outer retinal layers just off center lose thickness, and on autofluorescence the same zone glows differently. Neither change produces a symptom. That is precisely why annual imaging exists instead of an instruction to report blurry vision.
Pattern varies by ancestry. Most people of European descent show the parafoveal type, a ring close to the center. East Asian patients more often show the pericentral type. It sits further out, sometimes along the vascular arcades. Exceptions run in both directions, so a thorough screen looks for both. A protocol built around one population fails quietly in another.
Which Eye Changes Reverse and Which Do Not
Two very different things happen in the eye on hydroxychloroquine. Confusing them causes needless alarm. The reversible ones sit at the front and show up early. The permanent one sits at the back and shows up late.
Clears up on its own
Corneal whorls, the faint spiral deposits a slit lamp picks up in the surface layer. Blurred focus in the first weeks, from a temporary effect on the focusing muscle. Both fade. The whorls usually resolve within a month of stopping.
Does not come back
Retinal thinning from long-term accumulation. Photoreceptors do not regenerate. Damage can keep advancing for a year after the last tablet. Stopping halts the cause, not the consequence.
Corneal deposits deserve a word of their own. The term frightens people who meet it in a report. They form when hydroxychloroquine collects in the surface cells of the cornea, and only a minority of long-term users ever develop them. Vision almost never suffers. Nobody stops treatment over them.
Early blur is the other harmless one. It comes from a temporary effect on the focusing muscle. Reading distance shifts for a few weeks before settling back on its own.
A third category runs the other way entirely. In Sjögren’s syndrome hydroxychloroquine appears to help the eye rather than threaten it. A controlled study in Rheumatology International found dry eye symptoms improving on hydroxychloroquine. Later work saw tear film measures worsen when patients came off it. Dryness with an inflammatory driver may respond here. Anything that dries the surface pulls the other way, and a season of loratadine taken for allergic itching can quietly undo what the tablet gives back. That makes it worth reading beside low-dose doxycycline for meibomian gland disease.
None of this changes what happens at the retina. Front-of-eye effects and back-of-eye damage travel on separate tracks. Clear corneas say nothing about the state of the macula. Other long-term tablets book their own eye follow-up for entirely different reasons, and isotretinoin is watched for dryness and night vision rather than for the retina.
Hair Loss Weight Changes and Other Side Effects
Most people tolerate Plaquenil better than anything else in their regimen. Nausea and loose stools top the complaint list. They cluster in the first weeks and usually settle after that. Beyond the gut the list thins out fast:
- Hair thinning and color change — loss is uncommon and reversible, while lightening comes from an effect on pigment cells
- Weight — Plaquenil does not drive weight gain and some users lose a little, unlike the steroids often prescribed beside it
- Skin and mucous membranes — blue-grey pigmentation can appear on the shins, the face, or inside the mouth
- Sun sensitivity — burns arrive faster than expected, awkward in a lupus population already told to stay covered
- Low blood sugar — severe hypoglycemia is documented even without diabetes medication in the mix
- Heart rhythm — QT prolongation, and after many years a rare cardiomyopathy
The mouth findings surprise people. Plaquenil and teeth come up often in searches. The answer is that the tablet does not damage enamel. What it can do is tint the hard palate and the gum line a slate blue-grey. The change is purely cosmetic, and any dentist who has met it before recognizes the pattern immediately. It fades slowly once treatment ends.
Muscle weakness sits at the far end of the list. It creeps in across years rather than weeks. Climbing stairs gets harder, and so does lifting the arms overhead. Strength returns once the medication stops. The full adverse reaction profile is published on DailyMed.
What Not to Take Alongside Hydroxychloroquine
Four combinations call for real attention. One of them is an eye issue rather than a systemic one.
- Tamoxifen — the one pairing that changes the eye schedule rather than the prescription itself
- Insulin and oral diabetes medication — hydroxychloroquine lowers blood sugar on its own, so doses may need trimming
- Digoxin — blood levels rise, and heart rhythm medications generally add to the QT effect
- Antacids and kaolin — they block absorption, so leave four hours between them and the tablet
Methotrexate is the opposite case. Hydroxychloroquine and methotrexate are deliberately paired in rheumatoid arthritis. That combination is standard rather than risky. Most anti-inflammatory tablets sit alongside without conflict too, including diclofenac for joint pain. Alcohol carries no direct interaction. Heavy drinking still loads a liver already processing several medications.
Taking Plaquenil While Pregnant or Breastfeeding
This is one of the few immune medications that pregnancy keeps rather than removes. Stopping raises the odds of a lupus flare, and flares threaten a pregnancy far more than the tablet does. Rheumatology guidance across the United States and Europe supports continuing.
One situation carries a specific benefit. Women carrying anti-Ro antibodies face a risk of congenital heart block in the baby. Hydroxychloroquine appears to lower that risk. It argues for staying on treatment rather than for starting during pregnancy.
Small amounts of hydroxychloroquine pass into breast milk. The quantity reaching a nursing infant sits far below any treatment dose. Continued use while breastfeeding is generally considered acceptable. Anyone planning a pregnancy should raise timing early, since the long half-life keeps hydroxychloroquine present for months.
Disclaimer
This page is written for general information and does not replace personal medical advice. Dosing and screening intervals for hydroxychloroquine depend on body weight, kidney function and individual risk. Please discuss your own treatment with your prescriber or your ophthalmologist before changing anything. Other entries in our medication library cover the drugs that come with their own eye monitoring. Prices shown reflect current listings and may change.