Buy Toradol online — ketorolac tablets that take on migraine attacks kidney stone pain and post-surgical aches too sharp for pharmacy-shelf strength. The label puts its relief on a level with opioids. An anti-inflammatory delivers it, not an opioid. No sedation. No dependence, and no controlled-substance paperwork at the counter. What Toradol carries instead is a five-day ceiling. That single number explains most of how it gets prescribed.
On this page
Toradol Treats Migraine and Kidney Stone Pain
Moderately severe acute pain is the registered indication. In practice that means pain which arrives fast and has to be stopped fast. Renal colic sits at the top of the list. Migraine that has outrun a triptan comes close behind. So do the first days after surgery or a dental extraction. People who buy Toradol online are almost always treating an episode with a beginning and an end.
Emergency departments reach for this medication constantly, and the reason is mechanical. A kidney stone hurts partly because prostaglandins raise pressure inside the blocked ureter. Blocking their production lowers that pressure directly. Relief then addresses the cause instead of masking it. Opioids do nothing about the pressure at all.
Migraine follows a similar logic. Neurogenic inflammation around the trigeminal system responds to a potent anti-inflammatory. That is why Toradol appears in so many rescue protocols. Orthopedic work leaves the same signature, and so does the first night after a joint procedure.
Dental cases account for a larger share of these prescriptions than most people expect. An impacted wisdom tooth leaves inflamed bone behind, and that particular pain answers poorly to acetaminophen on its own. Oral surgeons often send patients home on a short course for exactly that reason. Swelling peaks around forty-eight hours, and relief needs to outlast it.
Several common searches point at uses this medication does not cover:
Chronic pain is where the boundary matters most. Someone managing osteoarthritis month after month needs an anti-inflammatory built for the long haul. That is what diclofenac tablets are designed to do. Toradol was never in that category. Its whole design assumes a short and violent episode.
Pill Form of Toradol and When Shots Win
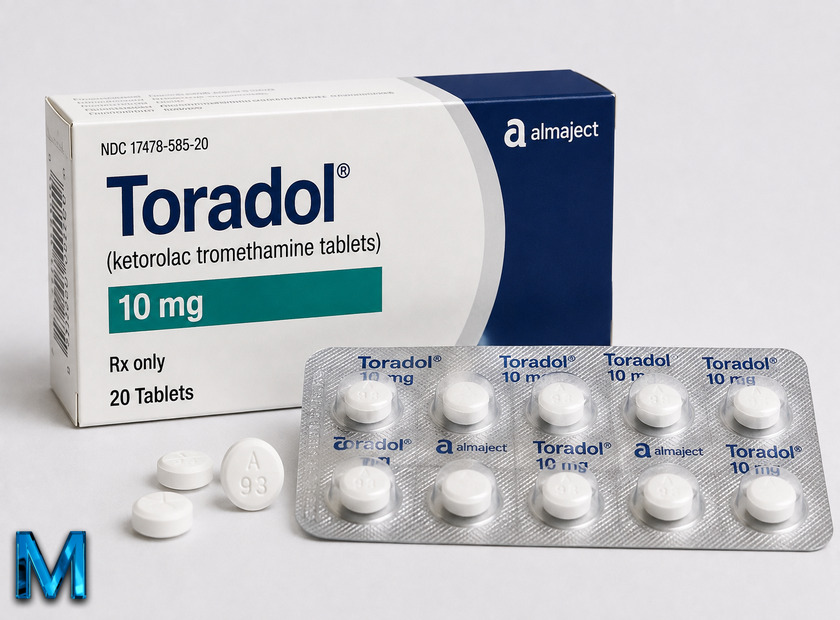
Yes, tablets exist, and the confusion around that is understandable. Nearly every mention of this medication involves a needle. The injection is what a clinic administers. Tablets come in one strength only: 10 mg. They are what a patient takes home once the acute peak has passed.
One detail in the label shapes everything here. Oral ketorolac is approved only as continuation treatment after an intravenous or intramuscular dose. It is never a standalone start. The prescribing information on DailyMed states this directly. A shot in the clinic, then tablets for the rest of a course capped at five days.
Route changes the arithmetic of a dose rather than the molecule itself:
Injections win on speed and on certainty. Someone vomiting through a migraine absorbs nothing from a tablet. A blocked ureter hurts far too much to wait. Tablets win on everything after that first hour. Nobody stays in a clinic for four days of scheduled doses.
How Fast a Toradol Shot Starts Working
Roughly thirty minutes for the intravenous route. Closer to forty-five for a shot in the muscle. Peak effect lands between one and two hours. Relief then holds for about six hours, which is why doses repeat four times across a day.
Tablets trail that curve by very little. Absorption is nearly complete. The peak arrives within an hour of swallowing. Food slows the climb without lowering the ceiling. Taking a tablet with a meal costs a few minutes and buys some protection for the stomach lining.
Half-life sits near five to six hours in healthy adults. Older patients clear it more slowly. Impaired kidneys slow it further still. Duration of effect stays fairly steady across ages even so. Relief depends on enzyme blockade, not on blood levels alone.
Toradol Dosage Tops Out at 40 mg a Day
Twenty milligrams for the first oral dose, then one 10 mg tablet every four to six hours. Never more than 40 mg across twenty-four hours. That ceiling is absolute for oral use. Doubling up during a bad afternoon does not deepen the relief. The enzyme it targets is already fully occupied at the standard dose.
Toradol behaves unusually in this respect. Most anti-inflammatories keep delivering a little more effect as the dose climbs. Here the analgesic curve flattens early while the risk curve keeps rising. Extra milligrams buy stomach and kidney exposure and nothing else. Prescribers treat 40 mg as a wall rather than a target.
Three groups skip that larger opening dose. Anyone past 65 begins on 10 mg instead of 20, and so does anyone under roughly 110 pounds. Impaired kidney function places a patient in the same category. The 40 mg daily ceiling itself does not move for any of them.
Spacing matters more than most schedules imply. Doses every six hours cover a full day within the four-tablet allowance, whereas a four-hour gap exhausts it by late afternoon and leaves the evening uncovered. Even spacing is the practical approach. Driving rarely enters the picture, since this medication produces no sedation of its own.
Matching tablets to a prescribed dose stays unusually simple all the same. Ten milligrams is the only oral strength on the American market, so every dose is counted in whole tablets and nothing needs splitting. Such simplicity is rare among prescription anti-inflammatories. Ibuprofen products alone span half a dozen strengths between shelf and pharmacy counter.
Why Ketorolac Courses End After Five Days
Risk accumulates while benefit does not. Ulcer and bleeding rates climb steeply with each extra day of exposure. The pain Toradol was designed for has usually faded by day three. Five days marks the point where the arithmetic stops favoring the patient. Every route counts toward that total.
A shot in the emergency room on Monday is day one, not day zero, and that catches people out. Tablets started on Tuesday therefore leave four days, not five. The label counts intravenous, intramuscular and oral exposure as one course. Restarting after a short gap does not reset the clock.
Evidence behind the limit came from postmarketing surveillance, not from theory. Bleeding complications rose sharply in patients kept on ketorolac past the recommended window. Elderly patients on longer courses accounted for a disproportionate share. Regulators wrote the boundary into the label itself. Clinical judgment was left no room to stretch it.
Longer relief has to come from a different molecule. That is the moment when a physician steps down to a gentler anti-inflammatory.
How Many Tablets a Single Course Uses
Twenty, at the very most. Four tablets a day across five days is the ceiling. Real courses usually land nearer twelve. The first dose came from a syringe, and pain often eases before day five. That number is the only sensible unit for comparing pack sizes.
Recurrence is what makes larger packs coherent. Kidney stones return for many people who have formed one. Migraine arrives on its own schedule. A surgical calendar can put two procedures in a single year. Someone with three or four episodes annually works through sixty tablets without ever breaking the five-day rule.
Nobody needs three hundred and sixty tablets for personal use. That quantity represents eighteen maximum courses. No legitimate treatment plan generates it. Count the episodes honestly, multiply by twelve to twenty, then buy the smallest pack that clears the result. Most people who buy Toradol online skip that step and pay for tablets they never open.
Buy Toradol Online and What Ketorolac Costs
Quantity is the only variable a buyer picks, which leaves price per tablet as the only honest comparison. Packs here open at $0.71 per pill and settle at $0.40 on the largest quantity. Pack totals flatter big boxes. They hide what a course actually costs.
Sellers quote totals across different quantities, which turns cross-shopping into guesswork. Each row below carries two numbers. The struck-through figure is the standard total. The bold one is what the order comes to.
Toradol pricing
Ketorolac tromethamine 10 mg — in stock
| Package | Per pill | Courses covered | You save | Per pack |
|---|---|---|---|---|
| 60 pills | $0.71 | 3 | — | $42.32 |
| 90 pills | $0.58 | 4 | $11.17 | $63.48$52.31 |
| 120 pills | $0.52 | 6 | $22.35 | $84.65$62.30 |
| 180 pills | $0.46 | 9 | $44.69 | $126.96$82.27 |
| 270 pills | $0.42 | 13 | $78.21 | $190.45$112.24 |
| 360 pills | $0.40 | 18 | $111.73 | $253.93$142.20 |
Read the third column before the last one. Two or three episodes a year clear the smallest pack comfortably. Tablets carry an expiry date like anything else. Packs beyond 180 suit only recurrent pain already managed by a physician.
American pricing gives that comparison its context. Retail without insurance runs near $30 for twenty tablets. A discount card typically brings the same fill to around $17. Sharper coupons occasionally land closer to $12. Measured per tablet, the smallest pack here undercuts the average coupon and trails the very best one. Published pharmacy figures shift week to week.
A coupon applies to one fill, and that is where the real gap opens. Because of the five-day rule that fill is twenty tablets. No counter dispenses a hundred and eighty ketorolac tablets at once. Somebody whose stones recur four times a year pays that price four separate times. Per-tablet cost survives every version of the comparison. It is the number worth carrying into any decision to buy Toradol online.
Roche retired the Toradol brand in the United States years ago. Every tablet on the market now carries the generic name. Generic manufacturing meets the same bioequivalence standard. The brand still carried decades of manufacturing history behind it. Price is where generics win outright, and no premium version is left to weigh against them.
Why Ketorolac Never Sells Over the Counter
Toradol over the counter does not exist anywhere in the United States. The reason sits in the label, not in pharmacy policy. Ketorolac carries a boxed warning covering gastrointestinal bleeding, kidney injury and hemorrhage. Nothing carrying that warning reaches an open shelf.
A second version of the question comes up just as often. Does an over-the-counter equivalent exist? Not really. Ibuprofen and naproxen sell freely and share the same class. Yet a single 10 mg tablet delivers relief closer to an opioid dose than to anything in the pain aisle. That potency is what keeps it behind the counter.
Cross-border searches follow identical logic. Toradol in Mexico and ketorolac in Canada both draw steady interest. Both countries classify it as prescription-only as well. Importing an unapproved supply into the United States is separately unlawful.
Anyone preparing to buy Toradol online can run five quick checks on the listing first:
- Tablet strength and pack quantity appear before checkout rather than after
- Price per tablet is shown alongside the pack total
- The generic name ketorolac tromethamine sits next to the brand name
- The five-day limit is stated somewhere on the page
- Nothing describes the medication as available without a prescription
That last point does most of the work. A seller who calls Toradol an over-the-counter product has revealed how much they know about it.
Is Toradol a Narcotic or Just an NSAID
Not a narcotic, not an opioid, and not a controlled substance in any state. Toradol is a nonsteroidal anti-inflammatory. Its relatives are ibuprofen and naproxen, not morphine. No prescription monitoring program tracks it. Nothing about it produces physical dependence.
Confusion on this point has understandable roots. The label describes analgesia at the opioid level, and that phrase alone sends people searching. Add the setting — a syringe, an emergency department, relief within half an hour. Resemblance to a narcotic becomes hard to shake. Hospitals reinforce it by using ketorolac specifically to lower opioid doses after surgery.
Reports of feeling loopy or drowsy usually trace elsewhere. Migraine protocols pair Toradol with sedating partners such as diphenhydramine or metoclopramide. Either one accounts for the fog far better than the anti-inflammatory does. Severe pain lifting suddenly also brings a light-headed relief that people misread as intoxication.
Comparisons with tramadol and hydrocodone measure different things. Those two act on opioid receptors in the brain. They carry dependence potential and appear on controlled schedules. Toradol blocks an enzyme in tissue and carries organ risk instead. Neither profile is gentler overall. The hazards simply live in different places.
Professional sport handed the name a second reputation entirely. Ketorolac injections became common in American football locker rooms as a way of returning players to the field. Concern grew far enough that the league’s physician society published a task force recommendation against giving it preventively to players who are not injured. Some people therefore associate the medication with masking injury instead of treating pain.
What Not to Mix With Ketorolac Tablets
Other anti-inflammatories head the list, and the rule holds no exceptions. Ibuprofen, naproxen, aspirin and prescription diclofenac compete for the same enzyme. Each of them stacks the same stomach risk. Relief does not improve. Bleeding risk climbs with every added milligram.
Acetaminophen is the exception people are usually looking for. It works centrally and leaves peripheral cyclooxygenase largely untouched. Pairing it with Toradol is a recognized post-surgical strategy, not a hazard. Combination products exist because the two mechanisms do not overlap.
Alcohol thins the protective mucus layer of the stomach by itself, and a potent anti-inflammatory arriving on top compounds that effect instead of merely adding to it. One drink across a five-day course is unlikely to change much. Regular evening drinking through the same window is a different proposition.
Five other categories change the risk calculation:
- Anticoagulants — warfarin, apixaban and rivaroxaban multiply an already elevated bleeding risk
- ACE inhibitors and diuretics — the combination strains kidney perfusion from three directions at once
- SSRI antidepressants — platelet function drops further and gastrointestinal bleeds become measurably more common
- Lithium and methotrexate — ketorolac slows their clearance and pushes blood levels toward toxicity
- Alcohol — the most common real-world contributor to stomach bleeding on any anti-inflammatory
Emergency migraine protocols look alarming on paper. In practice they are usually fine. Toradol arrives alongside metoclopramide for nausea, sometimes with diphenhydramine to blunt restlessness. Ondansetron occasionally takes its place. None of those act on cyclooxygenase, so the combination avoids the stacking problem. Steroids are a different matter. An oral course of dexamethasone at the same time raises gastric risk noticeably. Post-surgical steroid eye drops deliver too small a systemic dose to matter.
Ketorolac for Pain After an Eye Operation
Tablets and drops divide the work after cataract or refractive surgery, and they are not interchangeable at any stage. Drops handle inflammation on the ocular surface and inside the anterior chamber of the eye. Tablets reach the deeper ache around the orbit that topical treatment never touches. Some surgeons therefore send patients home with both.
Ophthalmic ketorolac has its own history under the names Acular and Acuvail. Surgeons use it to prevent cystoid macular edema. That is fluid gathering in the central retina, and it can blur vision weeks after a flawless cataract procedure. Nobody disputes the indication now. The American Academy of Ophthalmology covers where topical anti-inflammatories sit alongside steroids in the weeks following an operation. One combination product sends the same molecule straight into the eye during the procedure itself, mixed with phenylephrine to hold the pupil open.
Same molecule, different destination.
Corneal abrasion is the other place these drops turn up, and the reasoning there differs from cataract care completely. A scratched cornea hurts out of all proportion to its size, because the surface carries one of the densest nerve supplies in the body. Anti-inflammatory drops dull that pain without the healing delay a steroid would introduce. Refractive surgery borrows the same approach for the first day or two while the flap settles.
One risk belongs specifically to the topical route. Prolonged use of anti-inflammatory eye drops has been linked to corneal melt. That is a thinning of the corneal surface which in rare cases progresses to perforation. A case series published in Ophthalmology documented ulceration and perforation across sixteen patients. Dry eye, existing surface disease and long unsupervised courses raise the risk. Tablets carry no such hazard.
Steroid drops remain the backbone of post-operative eye care, and prednisolone acetate still does most of that work. Anti-inflammatories of this class are the addition, never the replacement. Vision recovers on the steroid, while the drops described here guard the macula in the meantime.
When to Stop Ketorolac Before an Operation
Twenty-four to forty-eight hours ahead for most procedures. Surgical teams generally ask for longer. Toradol suppresses platelet aggregation while it circulates. A tablet taken the night before an operation can still affect clotting on the table. Its short half-life means the effect fades faster than aspirin’s, though not instantly.
Cataract surgery sits at the low-risk end of that spectrum, since modern small-incision technique bleeds very little. Many eye surgeons no longer stop anti-inflammatories before routine cases at all. Oculoplastic work changes the calculation entirely. Eyelid and orbital procedures cut through tissue that bruises readily. Anyone facing either operation should raise current medications during the pre-operative assessment.
One contraindication is absolute and has nothing to do with timing. Ketorolac must never be used around coronary artery bypass grafting. That prohibition appears in the boxed warning itself. Bleeding risk in that setting proved unacceptable in trials.
Office procedures raise the question from the opposite direction. A dose before IUD insertion is one recognized approach to the cramping, and here the medication is given deliberately, because the aim is blunting pain instead of protecting a surgical field. Bleeding is negligible either way.
Other procedures fall between the extremes. Dental extraction, colonoscopy and outpatient orthopedic work all involve some bleeding. Standard practice is a pause rather than a full stop. Any restart afterward draws on the same five-day budget.
Inside the Boxed Warning on Ketorolac
Four hazards carry the strongest warning the FDA issues. Every one of them scales with duration. Gastrointestinal bleeding leads the list. Kidney injury, bleeding from suppressed platelets and cardiovascular thrombotic events follow it. MedlinePlus sets out the full warning in patient language.
Stomach damage arrives without warning symptoms in a meaningful share of cases. Ulceration can develop and bleed before any pain appears. Elderly patients account for most serious events. Black or tarry stools, blood in vomit, or sudden weakness after a dose all point to bleeding already under way.
Kidney injury is the easiest of the four to trigger. Toradol constricts the arterioles feeding the glomerulus, and anyone dehydrated, elderly, or on a diuretic loses the compensation that normally protects them. Reduced urine output, ankle swelling or unusual fatigue during a course are the practical signals. Damage from a short exposure usually reverses once the medication stops.
Cardiovascular risk applies to this whole class, not to Toradol uniquely. The five-day limit keeps exposure short enough that it rarely dominates the picture. Existing heart failure or uncontrolled blood pressure shifts that balance. A different anti-inflammatory then becomes the better choice.
Who Should Never Take Ketorolac
Several groups are excluded outright. These are formal contraindications rather than precautions:
- Anyone with active peptic ulcer disease or a history of gastrointestinal bleeding
- Patients with advanced kidney impairment or at risk of renal failure from volume depletion
- People whose asthma, hives or nasal polyps have ever flared after aspirin or another anti-inflammatory
- Women in labor and delivery, and during the third trimester of pregnancy
- Patients before or after coronary artery bypass surgery
- Anyone with a suspected bleeding disorder or incomplete hemostasis
- Children, since oral tablets are not approved for pediatric use
Nursing mothers sit in a separate category. Guidance there has shifted over time and depends on the infant’s age. Aspirin-sensitive asthma is the exclusion most often missed. That reaction can be severe. Many people never connect an old episode after ibuprofen to a whole class of medication.
Disclaimer
This page is general information about a prescription medication and does not replace personal medical advice. Talk to your doctor or pharmacist before starting, stopping or changing any treatment. That matters most for anyone on blood thinners or blood pressure medication.